
FASCIA TRAINING INSTITUTE | CLINICAL SCIENCE & PROFESSIONAL EDUCATION
Fascia and Lymphatic Flow Do Not Work in Isolation.
How connective tissue, lymphatic transport, breathing and brain-fluid dynamics shape pain, movement and recovery.
New research is changing how clinicians understand the relationship between fascia and the lymphatic system, interstitial fluid, breathing, pain and the brain. The Fascia Training Institute brings that science into a measurable clinical framework.
For practitioners, physicians, researchers, educators, and sports and performance organizations.

The symptom may be local.
The system producing it may not be.
Pain is often treated where it is felt. Swelling is treated as a separate problem. Movement is measured without asking what the tissue or nervous system had to change to create it.
THE CLINICAL MODEL
The old model isolates what the body integrates.
The body does not organize itself by professional specialty. Fascia, nerves, vessels, interstitial fluid and movement operate in the same physical environment. When one part of that environment changes, the effects may extend beyond the painful location.
SYMPTOM-LED TREATMENT
Sequence before assessment.
- Generic protocols replace clinical reasoning.
- Pressure is mistaken for precision.
- Range is gained without testing transfer or retention.
FTI CLINICAL FRAMEWORK
Assess. Target. Measure.
- Identify restriction, compensation and sensory response.
- Dose input to neurological capacity.
- Remeasure immediate change and functional transfer.
FASCIA, INTERSTITIAL FLUID AND LYMPHATICS
Where fascia and lymphatics meet.
The relevant interface is the connective-tissue extracellular matrix. It includes fascial tissue in some regions, but the evidence does not establish the same direct mechanical effect in every fascial tissue.
Fascia and extracellular matrix
Interstitial fluid environment
Initial lymphatic uptake
WHAT CURRENT EVIDENCE SUPPORTS
Initial lymphatic vessels are tethered to surrounding extracellular matrix by anchoring filaments. Changes in interstitial pressure and tissue deformation can help open overlapping endothelial flaps and permit fluid entry. Collecting lymphatics also depend on intrinsic contraction, valves, skeletal-muscle activity and other forces.
WHAT HAS NOT BEEN ESTABLISHED
This physiology does not establish that every fascial or myofascial technique increases lymph flow. Clinical effects depend on the technique, dose, tissue state and individual. Direct evidence remains limited.
LYMPHATIC TRANSPORT
Lymph does more than “drain toxins.”
The lymphatic system maintains fluid balance, returns proteins and fluid to the circulation, transports immune cells and absorbs dietary fats. Lymph movement is supported by intrinsic lymphatic contractions, one-way valves, skeletal muscle activity, joint motion, arterial pulsation, respiration, external compression and body position.
Respiratory pressure changes can influence lymph transport, but their effects vary. Breathing is one contributor, not a guaranteed treatment for lymphedema.


CLINICAL ACCURACY
Intervention must match the condition.
Manual lymphatic drainage may be useful for selected patients, but outcomes depend on diagnosis, disease stage, protocol and accompanying care. Evidence in breast-cancer-related lymphedema is mixed. After primary total knee arthroplasty, randomized evidence does not support routine early MLD for swelling, pain or knee motion.
The correct conclusion is not “MLD works” or “MLD does not work.” Intervention must be matched to the condition, delivered with precision and evaluated against a defined outcome.
GLYMPHATIC AND MENINGEAL LYMPHATIC RESEARCH
The brain’s emerging fluid-exchange network.
The glymphatic model describes cerebrospinal fluid movement along perivascular pathways, exchange with interstitial fluid and transport of metabolic solutes. Meningeal lymphatic vessels provide an additional route connecting the cranial environment with peripheral lymphatic pathways.
Sleep
Breathing
Mechanical coupling
EVIDENCE BOUNDARY — Fluid motion is not proven waste clearance. The exact routes, drivers and contribution of bulk flow, diffusion, vascular pulsation and aquaporin-4 remain under investigation. No human therapy has been proven to enhance glymphatic or meningeal-lymphatic clearance and improve health outcomes.
BREATHING, MOVEMENT AND PAIN
Breathing is a mechanical and neurological input.
Breathing changes pressure across the thorax and abdomen. These pressure changes influence venous return, peripheral lymph transport and cerebrospinal-fluid motion. Breathing also changes rib-cage mechanics and may influence autonomic state, muscle guarding, attention and pain perception.
Pressure. Regulation. Capacity.
Pressure: respiratory pressure is one input into peripheral fluid transport and cerebrospinal-fluid motion.
Regulation: breathing can change autonomic state, attention, muscle guarding and pain processing.
Capacity: movement and breathing capacity should be measured, not assumed.
Breathing does not “push pain out of the fascia.” It may change the mechanical and neurological conditions through which pain is processed. That is the stronger—and more defensible—clinical explanation.
THE FTI CLINICAL FRAMEWORK
Precision is a sequence of verified decisions.
The Fascia Training Institute does not teach practitioners to follow generic sequences. It teaches a disciplined process for creating and verifying measurable change.

01. Assess

02. Target

03. Respect load
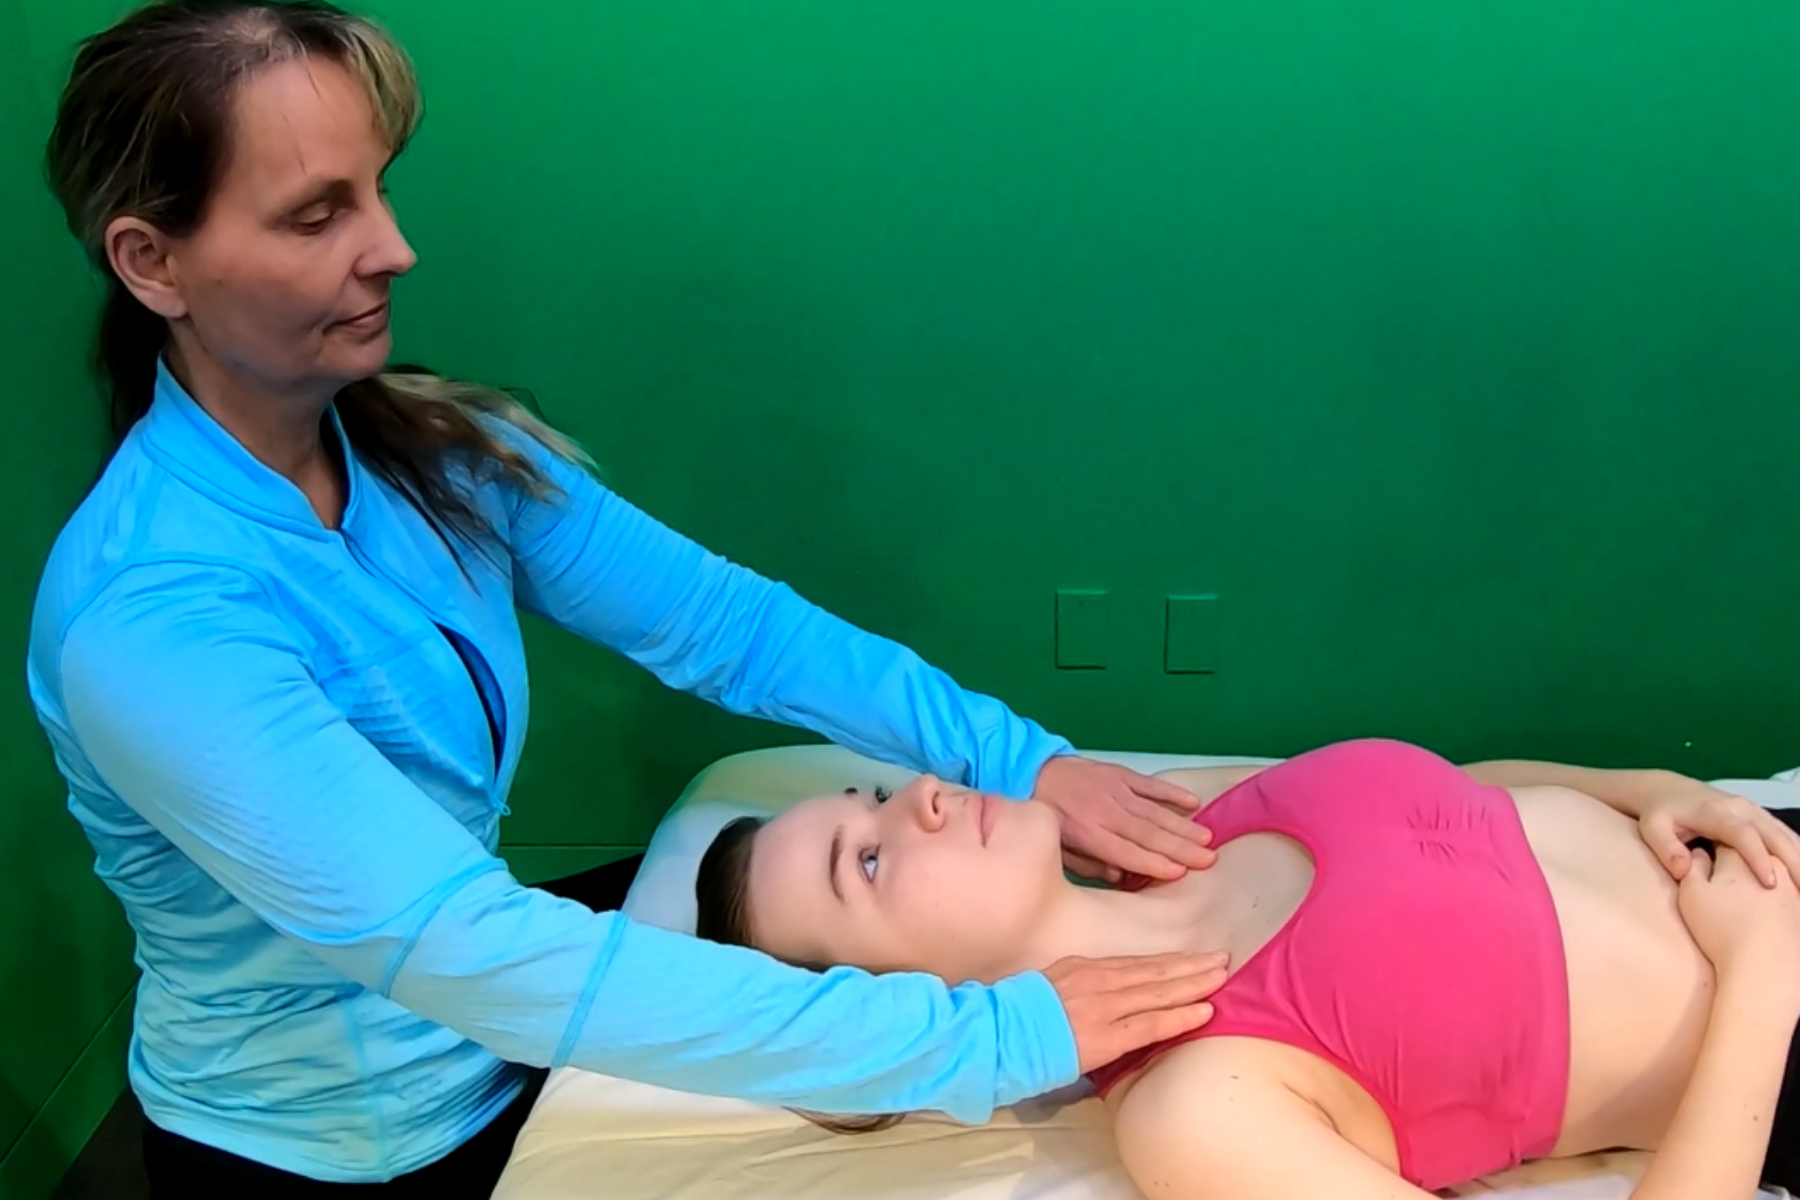
04. Remeasure
05. Confirm
Simone is the real deal. You need to speak with her.
After experiencing Simone Fortier’s work, Brad reported an immediate subjective difference in how his brain felt and how his body moved. The experience led him to speak directly with NHL Alumni leadership and opened a broader conversation about brain health, fascia, mobility and long-term player health.
Brad May’s statement describes his personal experience. It is not a guarantee of individual or clinical outcomes.
CLINICAL OBSERVATION AND RESEARCH
Clinical results should lead to better research.
Science does not advance by dismissing what clinicians observe. It advances when important observations are documented, measured and tested.
- Clinical observation generates the question.
- Measurement strengthens the observation.
- Research tests the explanation.
FOR INSTITUTIONS, EDUCATORS AND PERFORMANCE ORGANIZATIONS
Build an evidence-aware clinical standard.
The Fascia Training Institute welcomes serious conversations with healthcare professionals, universities, research groups, continuing-education providers, professional associations, sports organizations and rehabilitation departments.
We translate clinical observation into disciplined education, structured measurement and research-ready questions.
PARTNERSHIP PATHWAYS
- Professional practitioner education
- Curriculum and faculty collaboration
- Structured case documentation
- Clinical outcome measurement
- Research design and implementation
- Translation into sport, rehabilitation and human performance
CLINICAL QUESTIONS, ANSWERED PRECISELY
Frequently asked questions.
What is the relationship between fascia and the lymphatic system?
Lymphatic capillaries collect interstitial fluid from a connective-tissue environment. Anchoring filaments connect initial lymphatics to the extracellular matrix, allowing tissue pressure and movement to influence fluid entry.
Can restricted fascia cause swelling?
Swelling has many causes. Tissue mechanics, movement and interstitial pressure may interact with fluid transport, but swelling should not automatically be attributed to fascia. New, persistent, unilateral or unexplained swelling requires medical assessment.
Does breathing move lymph?
Respiratory pressure changes are one contributor. Intrinsic lymphatic contractions, valves, muscle activity, joint motion, arterial pulsation and body position also support transport.
Does deep breathing improve glymphatic clearance?
Deep breathing changes cerebrospinal-fluid motion in human imaging studies. It has not yet been proven to increase brain waste clearance or treat neurological disease.
Can manual therapy improve glymphatic function?
This remains a research question. No direct human evidence currently establishes that fascia or lymphatic treatment increases glymphatic clearance.
What are fasciacytes?
Fasciacytes are fascia-associated cells identified as producers of hyaluronan, a molecule important to sliding between fascial layers.
Should fascia treatment hurt?
No. Intense pain is not proof of effectiveness. Treatment dose should match the tissue, objective and person’s neurological tolerance.
How should change be measured?
Relevant measures may include range of motion, symptoms, balance, strength, breathing mechanics, task performance and retention of the result.
Educational information only. This page does not diagnose, treat or replace assessment of any medical condition.
FASCIA TRAINING INSTITUTE
Move Beyond Technique
Learn to assess the restriction, respect neurological
load, apply targeted input and verify change through measurable outcomes.
Reviewed September 2026. Evidence context: initial lymphatic physiology, manual lymphatic drainage evidence, human breathing and CSF dynamics, and locomotion and brain motion research.